 Posted by


September is Blood Cancer Awareness Month and as similar to last year I have prepared a detailed update to our site to promote WLAD with links to The Lymphoma Coalition along with various updates from myself.
12 months since our last WLAD and what a year we have had.
EHA 2026 Diagnostic Guidelines for Hodgkins Lymphoma Large B Cell treatment.
In 2024 I was invited to join the Lymphoma Coalitions Community Advisory Board on Hodgkin Lymphoma. This CAB brought patient advocates throughout the International community to discuss their treatment and discuss side effects both short term and long term along with discussing necessary questions that needed to be raised in the 2025 global survey. Following this meeting I was invited to participate as a patients voice to the EHA 2026 Diagnostic Guidelines steering committee ( European Haematology Association). These guidelines are the road maps used in European Oncology and Haematology to diagnose and treat patients. We needed to get some vital issues included and added to the guidelines some very much a target for me and the remaining points evidence based from the CAB. My interest was to get the EHA to recognise and include Tarc blood testing and DNA testing as a diagnostic tool. In June 2026 this work was published and is now the clinical diagnostic guidelines in Europe. https://onlinelibrary.wiley.com/doi/full/10.1002/hem3.70422
and the patirnt frienly edition
https://ehaweb.org/app/uploads/2026/06/Understanding-Large-B%E2%80%91Cell-Lymphoma-v8-online.pdf
For a change in procedures with this draft the committee agreed to review it annually as against every 5 years, this was unanimously agreed by the committee as evidence based reports in 2027 would show the short/medium and long term results of an alternative treatment called CAR’s T Cell. A big part of these committees objective is to recommend treatment that has proven benefits for the patient and obviously a better success rate. It is generally expected that CAR’s T Cell will replace Stem Cell Transplants for HLD Large B Cell Lymphoma in the years to come. These reports will be based on the 5 to 10 year monitoring from International trial centres. From listening to the committee they appear to be focused on placing CAR’s T Cell as the recommended procedure for relapsed patients, unfortunately they will need to include “where geographical available”.
This guideline includes all targeted points raised during the draft preparation part of my next mission is to help introduce Tarc test in Ireland. As Tarc is now mentioned as a diagnostic blood test it can be used in Lymphoma but needs to be introduced to Pathology units at an international level.
Car’s T Cell Therapy Ireland
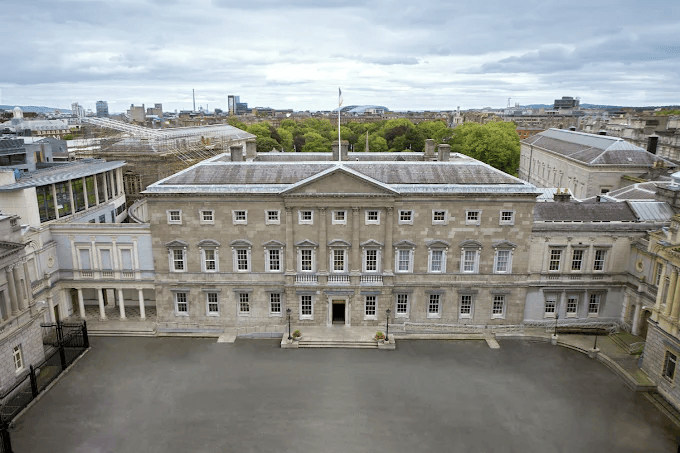
Through the Lymphoma Coalition I was linked in with Michael and Jan Rynne of CLL Ireland, Michael and Jan are also part of the coalition https://clli.ie/ with this connect I was introduced to Ms Margaret McCarthy, a patient advocate based in Cork Ireland. Mag’s has gone to exceptional lengths to highlight issues within the Irish health service with the serious lack of facilities in Ireland to provide treatment centres for Stem Cell Transplants (SCT), CAR’s T Cell therapy and more Gene therapy treatments. Ireland have only two centres of excellence for treatments with SCT, one in Dublin and the other in Galway, but only one for CAR’s T Cell in Dublin. This means a serious shortage for treatments coupled with long distances for patients to travel. On the 7th of October Mags will be presenting the issues in Leinster House (the home of the Irish Government) with medical specialist from the International Community and various patient advocates including myself. Mag’s has managed to include one of the founders of CAR’s T cell therapy Professor Bruce Levine, along with the president of the European Bone marrow management centre, to help push the re opening of the therapy centre in Cork University Hospital, the unit was closed in 2006 for upgrading and refurbishment but has remained closed since then and this facility needs to be opened urgently, as it remains closed and patients are dying as they can’t access the treatments. I have mentioned CAR’s T Cell in previous articles and will write another article based on CAR’s T Cell soon. Centres of excellence like this one can host many new Gene therapy treatments and provide life saving services along with clinical trials for research. My last article was about this meeting https://hlai.blog/2026/08/24/ms-margaret-mccarthy/ and following the meeting I will be publishing the outcome. It is important to note that continued research into CARs T cell present indications that this therapy could replace current aggressive chemotherapy and become the preferred first line treatment for multiple cancers, Ireland is not ready to be part of this vital future as the therapy requires special laboratories to engineer T cells
A face for radio
I rarely publish photos of myself and basically never do videos BUT never say never. The Lymphoma Coalition asked me to record a brief video relating to unexpected side effects during treatment and I agreed to do one based on “Balance” our little dog Alfie decided to appear in the video which is featured on the Coalition’s Site. This is real proof that I have a face for radio but thankfully Alfie was a good visual distraction. https://lymphomacoalition.org/world-lymphoma-awareness-day/?gad_source=1&gad_campaignid=24085542468&gbraid=0AAAAAodnyx7fMYsnylBRNVUJiqrvBs5V9&gclid=CjwKCAjwnvTUBhBoEiwAZNDxZ1l4rqW7LlROwxew81pSXbRaC9p46jhcQHz3NSZWCu_rOpjruKaVwRoCulEQAvD_BwE
However to prove the point Interviewed on Corks 96FM with PJ Coogan.
This is about the reopening of The Stem Cell Transplant unit in CUH and Mags McCarthy focus to bring Patient Advocates and medical professionals together to present our finds to the Irish Government to get the unit back open in Cork
In simple terms the biggest Hospital in the biggest county in Ireland does not have a Stem Cell Unit. They opened it in 2007 and closed it for refurbishment in 2008 and it still remains closed, patient have to travel to Dublin (170 mile) to get treatment. Mags McCarthy has organized a focus group including Patient Advocates and top medical professionals to present the issues as above on the 7th of October. This interview was intended to highlight the difficulties in travel and represents my first radio interview as a patient advocate.
Health updates
Over 9 years in remission and the bugger is still haunting me. In Ireland we have a national public health sector called the HSE, and an option for Private Medical Insurance. My parents took out a family policy when we were born. This policy covered all the family to private health care and by 1994 following the passing of my Dad I decided to approach the provider to get my own policy with immediate and continued cover, they accepted this and since then I have been covered. But like everything else this is not cheap. We see annual increases even on the basic plan that I have been on. It cost me €1,500 per year and when you’re on state benefits that’s a hard call, thankfully I get to pay it monthly. Apart from annual increases the cover also gets reviewed and some treatment are not included. Classic example are scans, originally the policy included scans but in the mid 2000’s this changed and scans were only covered if you’re admitted to hospital overnight. For a cancer patient scans can be done multiple times throughout the year. Cost range between €350 and €900 . Our HSE do cover scans but the waiting times are unrealistic as the scans all tend to be urgent and Oncologists need the information fast. Urgent and national public care would be fiction. I can’t knock the HSE, all my PET Scans were covered by public health care as well as private and these would cost between €2,500 and €4,000 most of what I have seen the cost has been €3,500 and with 11 of these since 2014 that’s about €38,500. We also have a list of specialist that are not covered following treatment. Again the cost range depending on their area of specialty can range from €250 to €500 per visit, most of the specialist have a reduced rate for follow up visits. I have an Oncologist, Urologist, Nephrologist, Vascular Surgeon, ophthalmologist, Hematologist, Endocrinologists and a few others along the way.
The team of specialist were appointed during treatments and each were important to keep me alive. But following most consultants meetings – blood test before and after, various scans and procedures – it’s a very long list. Total cost was estimated at €45,000 to the end of 2025 and now in 2026 for the first 6 months cost have been roughly €7,500 and that will most likely double before the year end. And here is a list of long term issues
- Kidney Stones since 1992
- Diverticulosis since 2008
- Cancer – HLD Stage 4 since 2014
- AAA first detected in 2014
- Diabetes due to treatment 2014
- Dental treatment since 2014 due to aggressive chemotherapy
- Eye problems cause in first HLD attack 2014
Thankfully I qualified for a medical card that has covered my GP and medication since June 2014 but that was a fight to get and included pushing the Irish Taoiseach (Prime Minister) as my GP was costing up to €60 a visit. I can’t blame cancer treatment on kidney stones as this started in 1992 but the treatment definitely increased Diverticulosis, constant changes in diets really attacked the colon. Dental treatment was definitely due to the radiotherapy in 2014 and BEAM treatment in 2017 as my gums were badly damaged during treatment. About €5,000 of the €45,000 are dental costs and that will also increase in the coming years. Diabetes is monitored but I remain borderline. Chemotherapy steroid induced diabetes 2014 landed me initially as Type 1 and took 8 months to drop to Type 2 but cleared since 2015 however this has been monitored every 6 months since and it is staying lower that the level necessary for medication an ongoing battle.
“Stand and deliver your money or your life”
I have written a number of articles about kidney stones and how we have tackled it. The operation in August 2025 was a big step in approach and the Urologist is brilliant but these little fuckers are still building, In Oct 2025 I had a CT Scan that showed both kidneys clear for the first time since 1992 but in recent scans they are back.
I have no regrets about dropping some of the specialist over the years, but following a meeting with my Urologist he voiced concerns about the AAA as it had increased in size again. He wrote to my GP to highlight this and the GP organized an ultrasound. The Ultrasound report recommended an urgent review by a Vascular Surgeon. This was then organized by the GP and an appointment was made to see a leading vascular specialist in Galway. Prior to the scan but on the same day the specialist needed a more detailed ultrasound called a dublex scan. My personal health insurance had a shortfall of €88 which I had to pay on the day. The consultant cost was €300 “CASH” as they said they did not have a card machine (seriously what century are we living in and what other business in Ireland would get away with demanding Cash). We got to the scan unit and had 4 people ahead of us, and soon another 4 behind us. The scan was preformed and the results sent to the consultants room. The 4 people that were ahead of us were also in the clinic for the same surgeon, and the people behind us also joined us. As each patient was called in I started to time their meetings and each seemed to last about 10 minutes. Now years of meeting medical professionals has taught me that they spend time before meeting the patient to overview medical history, this has caused delays as my history is both complexed and lengthy. But not this time, the consultant had escorted a patient to his secretary and opened the door to call me in. This was a red flag for me and he basically introduced himself and briefly looked at the scan, he then went “over 5 cm is dangerous” he asked to examine me and pushed hard on my solar plexus – this pressure would hurt anyone, “Well that needs urgent attention” so I asked why he pressed that spot and he simple said “It’s a pressure point for the AAA” He then returned to his seat and said “Ian this needs urgent surgery via a stent graft, the sent graft is a minimal intervention as against open surgery, the cost of this procedure is €20,000 and a hospital cost of roughly €19,000 pending recovery, as I am not fully affiliated with your private health care provider there will be a shortfall which my secretary will outline to you” I asked if I did not proceed what to expect? The answer “Most likely a rupture within 3 months” I hate scare tactics and yet another red flag, 9 ½ minutes and escorted out to reception and that’s when the real fun started. The secretary asked for the €300 fee and I handed it to her, which she placed in an envelope of the days taking, Anita mentioned later that the enveloped was packed with money. I was handed a receipt and another form, I looked over the form briefly and asked “What is this?” The answer was that she had booked me in for the operation on the 8th of September and the form had the procedure number that I needed to confirm with my health care provider for coverage ! and I asked what the figure at the end of the page was for, that was the shortfall for the not “fully affiliated” a fee of €3,000. I told her that I needed time to consider what was proposed and the answer “I have booked you in, we will need payment of the €3000 shortfall within 10 days either by a cash payment in the office or a wire transfer to the office account” I again stated that I need time to consider and I would call her the next day, So off home, Anita was in a slight state of shock but asked me what my thoughts were. This is normal for us to discuss, basically I said we can’t afford this and I don’t like or trust the surgeon, with a stent I would be monitored every 3 months for the rest of my life and placing trust in this guy felt wrong, it would add a further burden of roughly €1,200 per annum to my costs. By the time we got home I had decided against the procedure. I called my GP the next day and thankfully caught him, explained what had been discussed and that I was not in favor, he advised me to call my private insurance anyway to make sure I was covered and suggested we meet later in the week when he received the report from the surgeon. So I called the insurance company and discussed everything, they confirmed that I was covered but that yes the surgeon could charge a shortfall plus a €200 excess. I then called the surgeons office and asked for a few days pause on confirming as I needed to meet with the GP, I was told that pausing was not possible and I needed to confirm booking, so I cancelled the procedure and was told that if I changed my mind I would need to organize another meeting with the consultant and it could take 6 months to arrange another booking so I again confirmed cancellation. I meet the GP two days later and he showed me the letter that was sent, I read over it and told the GP that most of the letter was a work of fiction. We discussed options and I suggested a second opion from a different vascular surgeon, GP looked up a list of surgeons in Donegal but the nearest were in Galway or Dublin, we picked one in Dublin and the GP wrote to him immediately with copies of the scans and copy of the letter from the consultant. By the following Monday I had the appointment with a request to bring all relevant scan report with me for Wednesday of that week (which was last Wednesday), I arrived on time and was the only person waiting in the clinic, the surgeon had come out to the reception to get a copy of my file, about 20 minutes later he called me in. I produced further copies of scans, lists of medication and list of all procedures in my medical history. He examined everything in detail and asked very relevant questions, he looked straight at me and said “Ian based on everything you have shown me and the fact that this AAA is at 5.4cm I would not operate but I would make a final decision following a CT NTAP as that scan would give a clearer view of the issue” I asked him to explain his decision in greater detail “Basically the current scans were not 3 dimensional as against a CT NTAP that would add clarity, that he was also evaluating me, that I presented myself and appeared very fit for such a chronic medical history, he added that he was more used to older patients in poor health that needed immediate surgery, that the chances of a rupture would be 5 to 8% within 12 months and that surgery itself could result in death at a greater percentage” He went into a full explanation of the pros and cons of open surgery as against a stent procedure, and concluded by asking if I had any question ? I had a lot which included part of the scan report that I was unsure about, basically the scan showed a report on my right side Carotid Artery he looked closer at this part of the report and then looked through my medical history. “Ian basically the Carotid Artery is the vessel that supplies blood flow from your heart to your brain, this vein runs up the left side of your neck, he suggested that the radiotherapy from 2014 may have created the damage and that the vein was only working at 50% he classed this as more dangerous than the triple A as further decay to the vein could result is serious damage to the brain BUT he needed to refer this back to my Oncologist for him to make a decision” so the plan going forward, urgent CT NTAP to be organized by my GP, a detailed report from both the ultrasound and the CT NTAP to be sent to my oncologist and to monitor the AAA every 3 months going forward. Following the CT NTAP he would make a final decision on surgery. This meeting took 45 minutes and even though the decisions differed I felt more comfortable with the explanations and discussions. I left and headed over to visit my sister and a meeting with Michael from CLL Ireland,
Lots to think about on the 3 hour drive home. I went in with one issue and left with two. The neck really worries me and I am organizing a meeting with the GP to discuss. Where the GP at my last meeting had mentioned that he would be prepared to discuss a return to work I now feel that his mind will change. I also need to allow time for the entire team to communicate and start setting up scans etc, am I worried YES of course I am, I need to return to work as the well has run dry, all my work in awareness is voluntary and I really enjoy that work, but with mounting cost I need to start earning again. This is not just to cover medical cost but to continue keeping the house warm and food on the table, the fuel crises has added over €200 to the cost of refilling our home heating oil, prices of food have shot up and an average shopping bill has gone from €200 a week to €300 plus. The Irish government have made it clear that the upcoming budget will not add any relief or payments to disabled victims, The world has definitely gone mad.
For the first time in my life I am facing financial crisis that I can’t see a way out of. But most likely I will come up with some ideas which includes the sale of our house again. The ladder fall from painting the exterior is still hitting my left arm, so my refurbishment plans have been delayed, the outside painting is only half done and the weather is bad anyway, I think we had about 2 good days in August and I need another 2 good days now to complete the painting, I have managed to manicure part of the garden and again we need a few dry days to finish that. I just need to remain focused and sane which is difficult with all this crap going on but lets see what comes next, our wedding plans have yet again been placed on hold, everytime we go to organize this something jumps up to stop us, the first was in 2014 as we were planning to get married that June but with the cancer diagnoses and the therapy we cancelled, again in 2020 and COVID came in along with Anita’s cancer diagnosis and now we are yet again in trouble but this time Anita has her wedding dress so its just trying to figure out what’s happening medically and financially, in Ireland we need to give 3 months notice to obtain a wedding license and in most cases we can’t plan more than a month ahead.
I don’t think I will win the Mr Cheerful award this month and I was half and half about this publishment of this article but that seems to be the way my writing has gone. But in the awareness world sometimes it vital to discuss the possible long term effects and still try to keep your positive mental approach.
 Hodgkin’s Lymphoma Awareness Ireland
